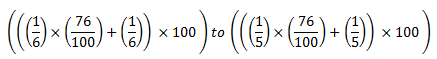Pages

Showing posts with label pregnancy. Show all posts

Wednesday, 17 June 2015

Endometriosis and Miscarriage


I’ve been hearing a lot in the news recently about endometriosis and miscarriage. I’ve seen reports on various news websites, which I won’t link to here because I noticed most of them are strewn with errors, the best summary is here on the endometriosis.org website.

I shan’t repeat what has already been written about the research too much, but I will try to add a few points that I think are worth addressing. Firstly, endometriosis and miscarriage (or any pregnancy complication for that matter) are serious problems and if one exacerbates the other that is cause for more attention to be paid to both. Given the fact that women with endometriosis can struggle to become pregnant, it is therefore extremely important for potential parents and medical professionals to know how best to care for pregnant women with endo if they are in a high risk group for any complications. 

To very quickly re-iterate the study’s findings; a group assessing the medical records of 5,375 women with confirmed endo and 8,280 women without endo between 1981 and 2010 from a database of records from all the state hospitals in Scotland found that the women with endo had a 76% increased risk of miscarriage. This is where I would like to make my first point. Hardly any of the reports on news sites make clear what that actually means, a 76% increase from what? It turns out miscarriages are more common than I thought and most occur during the very, very early stages of pregnancy. They may even occur before the woman even knows she’s pregnant. Of those women that do progress into pregnancy, depending on who you ask, the risk of miscarriage is around 1 in 6 to 1 in 5, which equates to 17-20%. So what does the 76% increase for women with endo actually mean?  It means the risk of miscarriage for women with endo rises to 30-35%. For anyone who wants to see the math (and I’m sure you do *sarcasm*) it goes like this 


There was also a noted increase in the risk of ectopic pregnancy in women with endo, a  2.7 times greater risk to be precise. The rate of ectopic pregnancies is much smaller than miscarriage, around 1 in 100. For women with endo then, this would increase the risk of ectopic pregnancy to around 3 in 100, a seemingly small, but nonetheless important, increase. 

This isn’t the first large study into adverse pregnancy outcomes in women with endometriosis which drew a similar conclusion. A study published in 2014 from Denmark analysed the records of 24,667 women with endo compared to 98.668 from endo-free women between 1977-2009. This study found the risk of miscarriage in women with endo rose to 24%, or around 1 in 4 women. This study also raised a good point regarding adverse pregnancy outcomes and the method of conception. Because of the subfertility experienced by women with endo, they are far more likely to undergo assisted reproductive therapy (ART) like in-vitro fertilisation (IVF). A study reviewing all current research on this topic was published in January this year and concluded that, for women with stage I-II endo undergoing ART the miscarriage rates were the same as the for endo-free women,  for women with stage III-IV though there was a lower rate of live births.

A deeper analysis is needed of the current data to really pull out some specific clinically relevant information. For example, as we have just seen, there may be a difference in pregnancy outcomes for women with different stages of endometriosis. Another issue to clarify would be does any specific hormonal therapy prior to conception have any effect on the outcomes. 

It would seem then that the evidence available certainly suggests that endometriosis is associated with an increase in adverse pregnancy outcomes. This information is most needed in the hands of obstetricians and midwives who can carefully monitor pregnant women with endo and react quickly to any warning signs that may endanger the life of the mother or child. 

A big question that remains then is why do women with endo have this increased risk? It is not simply enough to pay extra attention to pregnant women with endo, we need to know what causes the problems in the first place and how to correct them. Several studies, including my own research, have found that the endometrium in women with endo differs from that of endo-free women in several ways. Being as the endometrium is the point of contact for the developing embryo and its receptivity essentially dictates the embryo’s fate, more investigation is needed into endometrial alterations. Some studies have noted changes in the immune cells of the endometrium of women with endo, which may result in poor initial attachment of the embryo to the endometrium. This may then result in a decrease in viability of the developing foetus resulting in an increased risk of pregnancy loss. Further study is needed to discover how the endometrium of women with endo differs from endo-free women, how these differences affect the function of the endometrium and how this may be corrected.  

Friday, 28 March 2014

Endometriosis Awareness Month – Part 3


Endometriosis awareness month marches forward, quite literally. As you may have seen there have been awareness events taking place in many countries. Women with endometriosis and their supporters have been marching through major cities all over the world to help raise awareness for endometriosis and they have done an exemplary job.

Unfortunately I couldn’t make it to the UK event, but seeing the great turnout in all the cities and all the people who talked about it on Twitter/Facebook/blogs/forums etc, really showed just how much endometriosis awareness has changed for the better in the last decade. It certainly makes me hopeful for the future wellbeing of women with endo.

Speaking of the future, let’s have a look through some of the current research that will hopefully contribute to better prospects for women with endo everywhere.

We start then with a study from Denmark, which assessed the long-term reproductive status of women with and without endometriosis. To do this investigators examined medical records from tens of thousands of women across four national registries from 1977 to 2009.

 What they found was that, over the time course examined, women with endometriosis had around 7% fewer childbirths and 8% fewer naturally conceived children than women without endo. Not a massive surprise there; it’s well known that women with endo can find it difficult to get pregnant. Interestingly though the researchers found that as time went on (from 1980 to 1998), more women with endo had children, suggesting that it takes a long time for women with endo to conceive naturally (of course we must also remember that assisted reproduction wasn’t introduced until 1980). What is quite interesting is that they found that women with endometriosis were more likely to get pregnant with ART than women without by a small percentage.

This study also found that, for women with endo, the risk of ectopic pregnancy was twice that of women without. In addition, there were 21% more miscarriages in the group of women with endo. The reasons as to why this was the case remain unclear, it may be that the presence of active endometriosis in the pelvic area negatively affects pregnancy outcome somehow. Although, as the authors point out, there are other studies that have shown no increased risk of ectopic pregnancies in women with endo, so the jury is still out. In addition this study found that women with endo undergoing ART were at an increased risk of miscarriage, however another recent study found no increase in miscarriage risk. So whilst these studies are informative, they only represent the experiences of a certain population of women. 

One of problems with this study was that some of the women said to be diagnosed with endo, were only suspected to have it, not because they had laparoscopic diagnosis, meaning they may have had endo, or not, or another condition. Another issue is that this study wasn’t able to follow women throughout their entire reproductive life, so they didn’t have a complete picture of all the women’s reproductive history.

Nevertheless, what this study does tell us is that women with endo may require special prenatal care. If results such as these are the same in other countries it certainly suggests that additional provisions need to be made for women with endo (such as better monitoring of foetal and maternal health) and the medical community needs to be aware of this.

Moving on then, from the problems women with endo have to suffer with, to the ways in which the medical community is trying to solve those problems. Laparoscopic surgery is considered the best way of surgically removing endometriosis, but you need a good surgeon at the helm. Another problem is that not all endometriosis can be found and removed easily. One of the most troublesome forms of endo is deeply infiltrated endometriosis (DIE). This type of endo is very commonly associated with the most painful symptoms, such as chronic pelvic pain, painful sex, painful urination and painful bowel movements (depending on where the DIE is and how deep it has infiltrated).

Removing DIE is quite a challenge then, even for a skilled surgeon, which is why some surgeons are now trying robot assisted laparoscopy. Using ‘the robot’ does offer several advantages, such as better precision, better visualisation and more freedom to manoeuvre the instruments. Of course the downsides are that a surgeon will have to learn to use the robot and it is very, very expensive. Another point raised it that using the robot lacks a ‘tactile response’, that is, surgeons cannot feel the resistance or tension of some organs/tissues that might give them an idea of how to proceed with the surgery.

Therefore studies are needed to assess how well robot assisted surgeries fair in removing DIE. That is the subject of a recent paper from centres across the world.  This study looked at robot assisted operative results from 164 operations on women with DIE in different places to see how well the surgeons and patients faired.

Overall the average time for surgery was 180 minutes and the average hospital stay was 4 days, which, given the low rate of complications, seems like a long stay to me, but that may be due to different approaches to post-operative care in different centres/countries. 113 patients were followed up after an average of 10 months and 86.7% were found to be pain free, which is a god result by anyone’s standards.  

Other studies have shown that while robot assisted surgery takes slightly longer and is comparable in outcomes to conventional surgery with respect to stage I and II endometriosis, it may be beneficial for advanced stage endometriosis and has a lower risk of needing laparotomy.  

At the moment then the current evidence suggests that robot assisted and normal laparoscopy perform equally well in some respects, but that robot assisted surgery may be beneficial for women with advanced stage disease. However, more studies directly comparing the two surgical approaches are needed.

I will leave you then with an unusual case of endometriosis. A 52 year old man was sent for a CT scan after complaining about pelvic pain. What the doctors found was an inch long ‘cyst’ that, upon closer examination was found to be a tube like structure, with a muscular layer on the outside and an endometrial layer on the inside. Essentially this was a small uterus, but as it is displaced endometrium it still classifies as endometriosis (or endomyometriosis, to be technically correct). Unlike other male endometriosis cases, this patient hadn’t been undergoing any hormonal therapy and the man in question had no genetic or hormonal abnormalities that could account for this finding. In addition the patient had previously undergone surgery for a hernia near the area in which the ‘uterus’ had been found, so one would think this area of the body would have been examined thoroughly previously, indicating this problem may have arisen quite recently.

Tuesday, 30 April 2013

Research Roundup


Fresh from the success of endometriosis awareness month endometriosis research has continued apace. Unfortunately I’ve been quite busy lately so I haven’t had much time to write a detailed overview on any research this month. But, what I will do is briefly cover some of the highlights of endometriosis research that has been published over April.

To start us off is an article from South Korea looking into the effect of laparoscopic surgery for endo and its effect on the ability to conceive naturally. This study took 43 infertile women with endometriosis and followed up their conception rates 12 months after they underwent laparoscopic surgery to remove their disease. The overall result was 18 out of 43 women (41.9%) had conceived naturally after 12 months. As fertility issues are a major concern for women with endometriosis it is good to know surgical intervention can improve the likelihood of conceiving. (You can read the full article, for free, here)

Next is an encouraging piece of research looking at serious investigation into new treatments for the pain associated with endometriosis. This latest study from Brazil was a Phase II clinical trial (basically a detailed check to see if a drug works before it is put on the market) of melatonin for the treatment of endometriosis associated pain symptoms. You may have heard of melatonin before, it is produced by your body at different levels during the day and is responsible for telling your body when to wake up and go to sleep, but it also acts as an anti-inflammatory and analgesic. Results of this trial showed 10mg melatonin daily for 8 weeks reduced daily pain scores by 39.8% and dysmenorrhoea (excessively painful periods) by 38% also reducing the need for taking other pain killers by 80%. As an added bonus melatonin was also found to improve sleep quality with no severe side effects.

Next is a continuation of investigations into the relationship between environmental pollutants and endometriosis. All the conducted research thus far has failed to provide any conclusive proof of linking one type of pollutant to endometriosis. This latest study hopes to add some weight to the argument by exploring the relationship between Bisphenol A and 14 Phthalate metabolites in women undergoing laparoscopy or MRI. This study found that, in the women undergoing MRI, 6 phthalates were associated with a higher likelihood of being diagnosed with endometriosis. However, in women undergoing laparoscopy and histological confirmation (which is the superior diagnostic method) only two phthalates were found to be associated with an increased risk of being diagnosed with endometriosis. This study highlights the need for researchers to pay special attention to the way studies are conducted when looking at environmental exposures and endometriosis. From my own point of view I think it may be worth looking at younger girls when designing experiments. Every current study has been focussed on adult women with endometriosis, but if endometriosis is a condition you are born with (which the current evidence certainly suggests) then in-utero and early life exposures to pollutants will be more important.

I have written before about the relationship between ovarian endometriosis and ovarian cancer. Having ovarian endometriosis for a long period of time can increase your risk of ovarian cancer, but only by a very small percent. Nevertheless some women with endo may wonder what effects surgical or medical therapy may have on their ovarian cancer risk. A recent study from Sweden has done exactly that by examining medical records of women diagnosed with epithelial ovarian cancer at least one year after being diagnosed with endometriosis and calculating if surgical or medical therapies had any effect. What this study found was that women with endometriosis who had a single ovary removed, or had radical excision of all visible endometriosis, had a significant reduction in their ovarian cancer risk. This study provides further evidence that complete removal of all endometriosis should be a number one priority for all doctors dealing with the disease.

Quicker surgical intervention for endometriosis can only come from quicker diagnosis of endometriosis. This could be achieved with non-invasive tests for endometriosis before laparoscopy - identifying patients with a high likelihood of the disease in an objective way. I’ve reported previously about the current progress of non-invasive tests, but these are just stand alone tests; what if different non-invasive tests were combined? A study from Egypt has shown that combining a blood test for interleukin-6 (a substance produced in your body in response to infection or trauma) with a test for nerve fibres in the endometrium, can push the diagnostic sensitivity for minimal-mild endometriosis to 100% Clearly more research needs to be done in this area to validate these results, but in the future multiple tests from a single blood sample may be able to identify women with endometriosis.

It may seem fairly obvious to anyone who has any spent any length of time with, or near anyone with, endometriosis that the disease can severely impact the sufferers ability to work. However, just knowing its true isn’t enough, in order to convince policy makers, we need empirical evidence that endometriosis has an impact on a woman’s ability to work. What that means is we need scientific studies comparing women with and without endometriosis to show, in numbers and statistics, the true devastating effect of the disease. Fortunately there have been studies in the past conducted for this very reason and now there is another from Denmark. This study gave questionnaires to 610 women diagnosed with endometriosis and 751 reference women relating to health and work ability. Perhaps unsurprisingly this study found that endometriosis was associated with more sick days and low work ability, which in turn was associated with tiredness, daily pain and high pain levels. All obvious things you would think, but we need studies such as these to highlight the impact of endometriosis and get society and governments to take the disease more seriously.

That’s all I’ve got for this month, don’t forget to follow me on Twitter @EndoUpdateBlog for shorter, but more frequent, updates!

Tuesday, 29 March 2011

The Top Ten Bullshit Myths about Endometriosis

If you’ve suffered with endometriosis for any length of time chances are you’ve had plenty of advice from people, and chances are not all of it was helpful. One of the many problems with being an endometriosis sufferer is that some people, despite having good intentions, tend to have opinions that they feel the need to share with you despite the fact they don’t know what they’re talking about (this extents to certain members of the medical profession as well I might add). It also seems to be that the same spurious old wives tales keep being trotted out as fact and the same mistakes keep being made. It is a saddening fact but if you are a woman with endometriosis you have to become an expert on the subject, because so much crap gets thrown your way you have to learn how to deflect it. So, with that in mind and with a fair deal of inspiration from reading Cracked.com too much and a thread on the Endometriosis Research Center’s facebook page I present, in order of increasing capacity to irritate:

The Top 10 Bullshit Myths about Endometriosis

10) You can only get endometriosis in your pelvic area i.e. on the uterus and ovaries

Whilst it may be true that endometriosis is most commonly found on or around the uterus and ovaries, it is by no means exclusive to these areas. I put up a post in July last year that gave accounts of endometriosis in just about any area of the body you care to mention. Whilst It is a rare occurrence, extra-pelvic endometriosis is a very real, and in some cases, very serious problem. How endometriosis ends up in these areas is still a matter up for debate, however there have been several studies looking at cellular adhesion molecules (CAMs) in endometriosis. CAMs are like the anchors of a cell and depending on the expression of these CAMs cells can stick together or unstick themselves and move around the body. When cells end up moving around the body in this manner it is called metastasis, and is a characteristic of some cancer cells (when you hear of someone who’s cancer has spread, it can mean that the cancer cells have lost their CAMs and allowed the cells to move around the body). The studies mentioned above found that the expression of CAMs was abnormal in endometriotic cells, indicating they may be able to metastasise in a similar manner, possibly through the lymphatic system, thus explaining how you can get endometriosis in so many different places.

9) You can’t have endometriosis if you’ve had a hysterectomy

This one goes hand in hand with the whole ‘hysterectomy is a cure for endometriosis’ nonsense. Having a uterus is not necessarily a prerequisite for having endometriosis and removing the uterus certainly cannot be deemed a cure. To quote one study from the literature “probability of pain persistence [in the medium term] after hysterectomy is 15% and risk of pain worsening 3-5%, with a six times higher risk for further surgery in patients with ovarian preservation as compared to ovarian removal”. Recurrence of endometriosis is also very much dependant on the type of post surgical medical therapy used. If the ovaries are removed then unless you have already reached menopause chances are you’ll have to take hormone replacement, which carries an inherent risk of increasing the recurrence of the disease. It is therefore imperative that post-surgical medical therapy is careful managed.

8) You don’t need to be diagnosed, you can just take drugs to manage your symptoms

Let’s say you’re driving along one day when all of a sudden your car breaks down. You pull over to and call out a mechanic. The mechanic turns up, doesn’t open the bonnet but says “Yeh it’s probably the spark plugs”, he then proceeds to change the spark plugs. This doesn’t make the car start. So he says “Ah well in that case it’s probably the oil”, he then goes in and changes the oil. This doesn’t work either, so he carries on suggesting things that might be wrong without ever actually examining the engine properly, until eventually he might, by a process of trial and error, find something that works. Then you drive off without ever knowing what was wrong with your car or whether the problem will come back. Now, you wouldn’t accept this as a viable method of fixing a car so why would you accept this as a method of finding a treatment for a chronic illness? Yes the undiagnosed treatment may help relieve your symptoms but it doesn’t tell you what’s wrong in the first place. Many of the women I’ve talked to over the years spoke of a ‘sense of relief’ at diagnosis, because they had been suffering for so long they just wanted to know what was wrong. Diagnosing a disease acknowledges it is a real entity; knowing you are ill but not being able to put a name to the problem is like having the sword of Damocles dangling over you, with fear and uncertainty becoming mainstays of daily life. Aside from these issues, if endometriosis is not being diagnosed then how are we supposed to know how prevalent the disease is? If all doctors suddenly decided diagnosis was unnecessary then new cases of endometriosis will become zero, as you can’t report endometriosis unless there is visualisation at laparoscopy or histological diagnosis. What would this do for awareness or research for the disease? Not many people would be interested in a disease to which such a blasé attitude is taken. Endometriosis is the Schrödinger’s cat of diseases; it may or may not be there, so you have to open the box to check.

7) Wearing tampons causes endometriosis

I’m not sure where this myth came from. It may be that some people think that wearing tampons increases the amount of retrograde menstruation, but there is no evidence anywhere to support that. It may be that some people feel that toxicants present in tampons may lead to an increased risk of endometriosis. In this case ‘toxicants’ refers to our old favourite dioxin which may get into tampons via the bleaching process that the cotton undergoes. However, a study by the Food and Drug Administration (FDA) on the levels of dioxin in tampons found “most of the dioxins and furans were below the detection limit”. Another nail in the coffin of this myth is a further study which found that tampon use actually decreased risk of endometriosis. However, I will say that the methodology of this study wasn’t exactly perfect. I can’t get access to the full text and comments on this article, but the control group could have been better selected and a follow up would have given a much better insight into the consequences of tampon use. Nevertheless, I think we can safely say Myth Busted.

6) Endometriosis is caused by an infection, like an STI, which can be treated by antibiotics

We’re starting to move from simple misinformation to the just plain silly now. Most of the myths we’ve explored have at least been derived from some sort of logic (albeit horribly skewed). This myth is just nonsense and I suspect originates from confusion between endometriosis and endometritis, which is caused by infection of the endometrium by sexually transmitted or other types of bacteria. However, endometriosis and endometritis are completely different pathological entities so please feel free to correct anyone who confuses the two.

5) Only career women who have delayed having children get endometriosis

A different type of confusion here, this time its people getting confused between those who are more likely to get a disease and those who only get a disease. Yes, adult women between the ages of 21-35 are more likely to be diagnosed with endometriosis (note that I emphasised diagnosed because the symptoms of the disease often start a long time before diagnosis). There is also some evidence to suggest the more children you have the less risk of developing endometriosis you have. However, this is probably due to the suppressive (not curative) effect pregnancy can have on endometriosis, but more on that later. So although adult women who don’t have children are more at risk of endometriosis, this does not mean they are the only ones who have endometriosis. In fact if you think about it, endometriosis is a disease of adolescence. If most women with endometriosis get diagnosed in their mid-twenties and the diagnostic delay is, on average, 7-9 years, this means most women with endometriosis start experiencing symptoms in their teens, some women even get symptoms when they start their periods. It is extremely important to recognise and treat symptoms as an when they appear in young women, as highlighted by a recent study which showed young women who did not remain on treatment for their pain symptoms wound up with a more advanced stage of endometriosis. A great article on endometriosis and adolescents can be found here. The description of endometriosis symptoms presenting in an 8 year old girl certainly raised an eyebrow.

4) Endometriosis can be caused by psychological trauma in early life/ it’s all in your head

Easily this is the one that riles me more than any other stupid thing said about endometriosis. The only reason this isn’t number one is because I don’t hear it as often as the last two. Lets address the ‘it’s all in your head’ bullshit first as it’s the easiest to dismiss. Take at look at these pictures here, here and here, print them off if you like and carry them around with you. If anyone claims ‘it’s all in your head’ show them the pictures and ask “does this look like it’s in my head, does it, DOES IT?” scream it in their face should you feel the urge, beat them with a sock full of marbles if you wish, knowing full well the absurdity of your actions matches the absurdity of their statement. This attitude also puts the blame on the sufferer, which is sickening in itself. If you have endometriosis it is not your fault, it’s not like cutting your arm off while juggling chainsaws. It is my firm belief that for most women, the decision on whether or not you will have endometriosis is made before you were even born.

The whole ‘endometriosis is the result of early life psychological trauma’ argument is based on a couple of now widely discredited studies by a research group who really didn’t know what they doing in the first place, but those who find it suits their agenda will trot out this nonsense and cherry pick data to fit their augment, ignore these people, they are idiots. But let’s deconstruct it anyway; let’s imagine that endometriosis was a result of childhood trauma, how would reconcile this with the finding that endometriosis can clearly be a genetic disease? How would you explain endometriosis being found in unborn foetuses? How would you explain that the majority of women with endometriosis haven’t experienced childhood trauma? Some women with endometriosis will have experienced traumatic events in their childhood, but is it right for someone to suggest the two are linked when no evidence exists to support this? I am fortunate enough to have had a (relatively) normal childhood so can only offer my utmost admiration and respect those who have had it so much worse yet find ways in which to get the support they need and cope with what happened to them. Is it not therefore, a metaphorical slap in the face for someone else to come along and tell these brave people that the reason they have endometriosis is because they haven’t coped well enough?

3) If you have minimal disease you’ll only have minimal symptoms

As with so many other statements made about endometriosis, the answer to this one is simply ‘endometriosis doesn’t work that way’. At the very least this myth is based around some logic. If you hear the term ‘advanced disease’ and ‘minimal disease’ you may logically deduce that the advanced disease has the more serious symptoms. The trouble is endometriosis is not a logical disease. There have been a few studies which assessed the severity of symptoms of women with different stages of endometriosis and concluded that stage of the disease is not related to the severity of symptoms. Complicating the issue is the fact that is it’s not just the extent of the disease that leads to pain but the type of disease. If you follow this link you can find descriptions and images of the various types of endometriosis and one thing that may strike you initially is how many different types there are. Deeply infiltrating endometriosis (DIE) is a good type to use as an example of why this myth is false. DIE has been reported as a being significantly associated with severe dysmenorrhoea and the most painful type of endometriotic lesion as well as being involved the painful bowel and bladder symptoms associated with endometriosis. The trouble with DIE is that the lesions themselves can be relatively small and therefore, hard to detect and remove (there is a good free-text article here). DIE is like a garden weed, cut off the leaves and the roots remain, meaning incomplete removal of DIE can lead to a higher likelihood of disease recurrence. Why is DIE so painful? It is thought that, because this type of endometriosis buries into an organ, it puts pressure onto the nerves within the tissue and distorts the structure of the affected organ. This is a particularly significant source of misery when DIE is involved in the bowel.

2) Endometriosis is just bad period pains

I’m not a very good cook, I can just about manage to make cheese on toast without a trip to the burns unit. Therefore, with my limited knowledge on cookery, I don’t walk into restaurants and stand next to the chef saying things like “You’ve over seasoned that”, “I think that steak is overdone” or “that’s not how you make a pie”. The reason I don’t do this is because, as someone who doesn’t know what they are talking about when it comes to cooking, I shouldn’t be professing on that subject. It is very much the same thing whenever you hear someone say “endometriosis is only bad period pain”. Clearly, a person who says this doesn’t know much about endometriosis, they don’t have the disease and have probably never even spent much time in the company of someone who suffers with it. So why are they professing on the subject? Chances are these people just need some educating. Endometriosis is so much more than period pain; a great deal of women with endometriosis experience tremendous pain before, during and after their periods. Some would scoff at this “well its only period pain” they will say, “how painful can it be?” Well of course I couldn’t say, but my mother who suffered at the hands of endometriosis for many years described the pain as “worse than childbirth” so that should shut up any naysayers. But with endometriosis there are different kinds of pain, probably more than other people will experience in their lives. Common examples include: dysmenorrhoea (painful periods), chronic pelvic pain (defined as 3 months of continuous, nonmenstrual pain), dyspareunia (painful sex), dyschezia (painful bowel movements), dysuria (painful urination), back pain, leg pain, and shoulder pain.

The old saying goes, misery loves company, and endometriosis, being a herald of misery, is no exception as there are also co-morbid conditions to consider. Co-morbid conditions are conditions that are frequently found to be more common in women with endometriosis. Some examples of common co-morbid conditions include: Irritable bowel syndrome, fibromyalgia, fibroids, adhesions, migraine, chronic fatigue, interstitial cystitis, excessive menstrual bleeding, depression, anxiety and reduced fertility. The list of reasons why endometriosis is more than just painful periods is as long as my arm and I’ve got very long arms.

1) Pregnancy is a cure for endometriosis

Our number one is something I hear all the time. I don’t know a single endometriosis patient that hasn’t been told this at some point, or at least knows someone who’s heard it. I hear it on the television, I read it in news articles, I hear it from doctors and laymen alike and yet for all its universal saturation in our collective consciousness, the statement “pregnancy is a cure for endometriosis” is bullshit. Where this myth originated from I’m not sure, but it was probably derived from the observation that some women with endometriosis experience temporary suppression of their symptoms during pregnancy. I’ve spoken to a few women who have experienced reduction of symptoms during pregnancy, but I can honestly say I’ve never heard of single case of endometriosis being cured by pregnancy. Most women find that, although you may get symptomatic relief for 9 months, the pain does eventually come back. In point of fact a study of 345 women with endometriosis found that symptoms significantly increased postnatally for first time mothers.

Another major point here is the inappropriateness of this advice. I know several young women, who from the age of 16 were told to get pregnant by their doctors to alleviate the symptoms of endometriosis. Is it ethical or moral to give such advice to young girls? Having a baby should be choice made between loving adults who are emotionally ready for the lifelong commitment, not a quick fix solution to a chronic illness that doesn’t even work anyway! Also, many women with endometriosis suffer with subfertility or infertility, advising them to get pregnant is along the same lines as telling a wheelchair bound person they can cure their paralysis by going for a jog.

Well, that went on for much longer than I anticipated, but hopefully some of it has been enlightening, it is not a complete list of all the bullshit I’ve heard about endometriosis, rather just a collection of the top ten comments I hear most often and infuriate me the most. I hope there will be a time in the future when myths like these are confined to the same section of medical advice as demonic possession as the cause for mental illness. Educating yourself and others about endometriosis is an empowering endeavour and, if you suffer from endometriosis, a necessity. The more you know, the stronger you are, read the evidence, uncover the truth, ignore the bullshit.